Clinical practices and access to therapies for breast cancer in Latin America: results of a panregional survey by the Latin American Breast Cancer Association
Victor Acosta Marín1,2, Fernando Petracci3, Denis U Landaverde4, William Mantilla5, Cynthia Villarreal6, Guianeya Santander7, Agatha Reyes8, Joel Moreno9, Ahmad Wali Mushtaq10, Brizio Moreno11 and Juan Carlos Samamé12
1Department of Breast Surgery, Centro Clínico de la Mama, Caracas, Venezuela
2Department of Breast Imaging and Mastology, Centro Clínico de Estereotaxia (Ceclines), Caracas, Venezuela
3Department of Medical Oncology, Instituto Alexander Fleming, Buenos Aires, Argentina
4Department of Medical Oncology, Hospital México, CCSS, San José, Costa Rica
5Department of Medical Oncology, Fundación CTIC, Centro de Tratamiento e Investigación sobre Cáncer, Cundinamarca, Colombia
6Department of Medical Oncology, Breast Cancer Center, Hospital Zambrano Hellion – Tecnológico de Monterrey, San Pedro Garza García, México
7Department of Medical Oncology, Hospital Militar Uruguay HCFFAA, Montevideo, Uruguay
8Department of Medical Oncology, Hospital Roosevelt, Guatemala, Guatemala
9Department of Medical Oncology, Instituto Oncológico Nacional, Ciudad de Panamá, Panamá
10Department of Surgical Oncology, Hospital Eugenio Espejo, Quito, Ecuador
11Department of Medical Oncology, Hospital Regional ISSSTE, León, Guanajuato, Mexico
12Department of Medical Oncology, Clínica San Felipe, Lima, Perú
Abstract
Introduction: Breast cancer remains the most frequently diagnosed cancer and the leading cause of cancer-related death in women worldwide, with incidence and mortality patterns in Latin America that differ substantially from high-income settings and vary considerably across countries within the region. Characterising current clinical practices and access to innovative therapies is essential to identify care gaps, inform regionally adapted guidelines and improve equity in cancer outcomes.
Methods: A cross-sectional, web-based survey was conducted among 223 breast cancer specialists from 20 Latin American countries between October and December 2025. This study was conducted and reported in accordance with the Checklist for Reporting of Survey Studies The structured questionnaire, developed by an expert panel from the Latin American Breast Cancer Association, explored three conceptually linked domains: response assessment (routine use of functional imaging), axillary management in specific post-neoadjuvant clinical scenarios and perceived commercial availability of targeted therapies for advanced breast cancer. Data were analysed using descriptive statistics.
Results: Of the 223 respondents, 64.5% (N = 144) routinely used functional imaging to assess neoadjuvant treatment (NAT) response. Pre-NAT marking of the metastatic axillary lymph node in cN1 patients was not performed routinely by 57.1% (N = 127). In hormone receptor-positive/ypN0(sn) patients undergoing breast-conserving surgery after NAT, 53.9% (N = 120) opted for regional nodal irradiation plus whole-breast radiotherapy. For human epidermal growth factor receptor 2 -positive and triple-negative tumours with residual macrometastasis in a sentinel lymph node, management strategies varied substantially; axillary radiotherapy alone was the most frequent choice (55.9% and 47.7%, respectively). Trastuzumab deruxtecan was reported as commercially available by 74.7% of 162 respondents, whereas sacituzumab govitecan (25.9%), capivasertib (15.4%), inavolisib (4.3%), alpelisib (19.8%) and elacestrant (8.6%) showed markedly lower availability.
Conclusions: This survey reveals substantial variability in post-NAT axillary management and pronounced disparities in access to novel agents across Latin America, even as certain evidence-based practices, such as routine functional imaging, are widely adopted. These findings underscore the need for regional consensus guidelines, structured educational programs and health policies targeting access barriers to high-quality breast cancer care.
Keywords: breast neoplasms, neoadjuvant therapy, sentinel lymph node biopsy, Latin America, health services accessibility, surveys and questionnaires, axillary management
Correspondence to: Denis U Landaverde
Email: denislandaverde@gmail.com
Published: 24/09/2026
Received: 12/03/2026
Publication costs for this article were supported by ecancer (UK Charity number 1176307).
Copyright: © the authors; licensee ecancermedicalscience. This is an Open Access article distributed under the terms of the Creative Commons Attribution License (http://creativecommons.org/licenses/by/4.0), which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Background
Breast cancer is the most commonly diagnosed cancer in women worldwide and the leading cause of cancer-related death among them, with ~2.3 million new cases and nearly 685,000 deaths recorded in 2022 [1]. In Latin America, ~210,000 new cases and 66,000 deaths are attributed to breast cancer annually [1], and the region is characterised by marked heterogeneity in socioeconomic conditions, healthcare infrastructure, cultural factors and regulatory frameworks, which translate into substantial variations in clinical practice, stage at diagnosis and access to therapeutic innovation.
Neoadjuvant treatment (NAT) is a fundamental strategy in locally advanced and high-risk early-stage breast cancer, offering the opportunity to reduce tumour burden, improve surgical options, assess in vivo response and guide personalised adjuvant decisions [2, 3]. International guidelines, including the St Gallen Consensus and National Comprehensive Cancer Network guidelines, provide evidence-based recommendations for the neoadjuvant setting [5, 8]; however, their implementation across Latin America varies considerably owing to differences in access to imaging technologies, targeted therapies and specialised training [4]. Accurate assessment of response to NAT and appropriate axillary management are critical steps that directly impact prognosis and patients’ quality of life. In addition, the rapidly evolving therapeutic landscape, with the approval of new targeted therapies and immunotherapies, poses challenges for implementation and access across different regions [4].
Despite the existence of international guidelines, adoption of these recommendations can vary substantially between countries and specialised centres in Latin America due to factors such as technology availability, uneven drug supply, specialist training and regulatory frameworks. Knowing and understanding these practices and the current status of access to innovative drugs are essential to identify areas for improvement and to develop regionally appropriate strategies to optimise breast cancer care.
The Latin American Breast Cancer Association (LABCA) is dedicated to improving breast cancer care in the region through education, research and the promotion of updated guidelines and practices, with the participation of numerous leaders from Latin America and around the world. In this context, a panregional survey was conducted among breast cancer specialists in Latin America. The objective of this study was to describe current clinical practices related to assessment of response to neoadjuvant therapy, axillary management and the availability of drugs for breast cancer treatment across countries in the region. The results of this survey were presented at the Ancillary Meeting on Breast Cancer in Latin America of the San Antonio Breast Cancer Symposium (SABCS) 2025, ‘From evidence to daily practice based on access’.
Methods
Study design and population
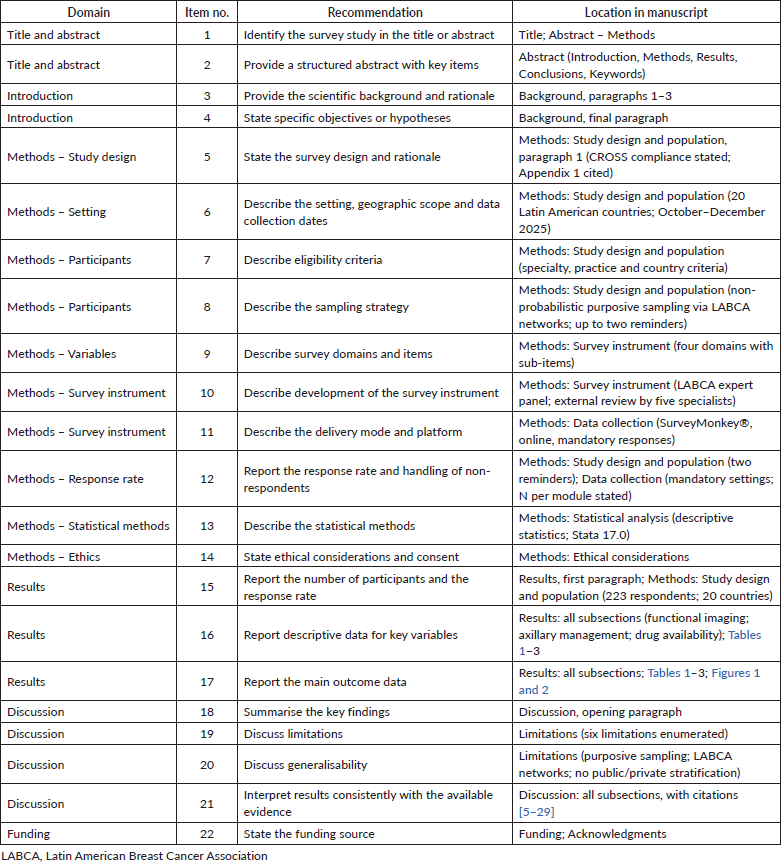
This descriptive, cross-sectional study was conducted and reported in accordance with the Checklist for Reporting of Survey Studies guidelines for survey research (Appendix 1). The target population comprised active breast cancer specialists practising in Latin America. Eligibility criteria required that respondents (a) hold a medical degree with specialisation in medical oncology, breast surgery, radiation oncology or pathology; (b) dedicate a substantial proportion of their clinical practice to breast cancer care and (c) be currently practising in one of the targeted Latin American countries. Participants were recruited through a non-probabilistic, purposive sampling strategy via the professional networks of the LABCA and allied regional oncology societies. Digital invitations were sent by institutional email lists and professional messaging platforms, with up to two reminders dispatched to non-respondents at two-week intervals. A total of 223 specialists from 20 countries completed the survey: Argentina, Bolivia, Brazil, Chile, Colombia, Costa Rica, Cuba, Ecuador, El Salvador, Guatemala, Honduras, Mexico, Nicaragua, Panama, Paraguay, Peru, Puerto Rico, the Dominican Republic, Uruguay and Venezuela. Given the purposive sampling through LABCA-affiliated networks, the final sample may over-represent academic and specialist-oriented practices; this is acknowledged as a limitation.
Survey instrument
A structured questionnaire was developed iteratively by a multidisciplinary panel of breast cancer experts from LABCA, comprising medical oncologists, breast surgeons and radiation oncologists. Item generation was based on a review of current international guidelines and areas of identified practice variability in Latin America. The draft instrument was reviewed by five external specialists not involved in item development; their feedback was incorporated before the survey was finalised. The questionnaire explored four main domains as follows.
Assessment of response to NAT: Routine use of functional imaging studies, including breast magnetic resonance imaging (MRI), contrast-enhanced mammography and positron emission tomography/computed tomography (PET/CT).
Axillary management in the neoadjuvant setting: The practice of marking (clipping) the metastatic lymph node in patients presenting with a clinically positive axilla (cN1) prior to initiating NAT.
Management of complex post-neoadjuvant axillary scenarios
Patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative invasive ductal carcinoma (IDC), initially cN1, who achieve a pathological complete response (pCR) in the sentinel lymph node (ypN0sn) after NAT and undergo breast-conserving surgery (BCS).
Patients with HER2-positive or triple-negative (TN) IDC who have residual macrometastasis in a sentinel lymph node (one out of four nodes) following NAT.
Market availability of innovative therapies: Perceived commercial availability of cyclin-dependent kinase 4/6 (CDK4/6) inhibitors (ribociclib and abemaciclib), poly(ADP-ribose) polymerase (PARP) inhibitors (olaparib), antibody–drug conjugates (trastuzumab deruxtecan and sacituzumab govitecan) and other targeted agents (capivasertib, inavolisib, alpelisib and elacestrant) in each participant’s country.
Data collection
The survey was administered online via SurveyMonkey® (SurveyMonkey Inc., San Mateo, CA), a validated, secure and Health Insurance Portability and Accountability Act-compliant platform. Mandatory response settings were applied to all items to minimise missing data; consequently, item-level response rates for mandatory questions were 100%, except for the drug-availability module, which was presented as an optional section completed by respondents who confirmed experience with prescribing or observing access to the listed agents (N = 187 for CDK4/6 and PARP inhibitors; N = 162 for antibody–drug conjugates and other targeted agents). Participation was entirely voluntary and anonymous. No personally identifiable information was collected. Data were exported, de-identified and tabulated for statistical analysis.
Statistical analysis
Data were analysed using descriptive statistics. Categorical variables were summarised as absolute frequencies (N) and relative frequencies (%). Results are presented as percentages with the corresponding denominator (N) for each survey item. For drug-availability questions, denominators reflect the subset of respondents who completed that optional module (N = 187 for CDK4/6 and PARP inhibitors; N = 162 for antibody–drug conjugates and other targeted agents). Missing data were minimal owing to the mandatory-response design and were not imputed. All statistical analyses were performed using Stata (version 17.0, StataCorp LP, College Station, TX).
Ethical considerations
This study involved the collection of anonymous survey data from healthcare professionals regarding their self-reported clinical practices. As no patient data were collected and participation was entirely voluntary, formal approval from an institutional review board was not required. All participants were informed of the purpose of the survey, and implied consent was assumed upon completion and submission of the questionnaire.
Results
Use of functional imaging to assess response to NAT
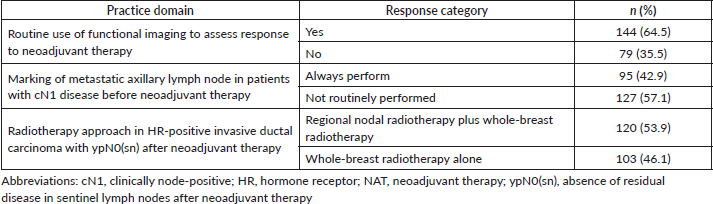
Of the 223 specialists surveyed, 64.5% (N = 144) reported routinely using functional imaging (breast MRI, contrast‑enhanced mammography or PET/CT) to assess disease response to NAT. In contrast, 35.5% (N = 79) do not incorporate these tools into their routine practice (Table 1)
Marking the metastatic axillary node in cN1 pre‑NAT
The practice of marking (clipping) the metastatic lymph node before treatment in patients with a clinically positive axilla (cN1) who will receive NAT was split. Of the specialists, 42.9% (N = 95) reported always performing this procedure, while a majority of 57.1% (N = 127) do not do it routinely (Table 1).
Axillary management post‑NAT: Clinical scenarios
Scenario 1: HR‑positive IDC, axilla cN1 pre‑NAT, ypN0(sn), BCS
In this scenario of excellent response to neoadjuvant therapy with negative sentinel lymph nodes, recommendations for additional axillary management after BCS and sentinel lymph node biopsy (SLNB) were as follows: 53.9% (N = 120) of specialists would choose regional nodal radiotherapy plus whole‑breast radiotherapy, and 46.1% (N = 103) would choose not to irradiate the nodes, limiting treatment to whole‑breast irradiation (Table 1).
Table 1. Clinical practice patterns in neoadjuvant treatment response assessment and axillary management among surveyed clinicians
Scenario 2: HER2‑positive IDC, SLNB with one node showing macrometastasis post‑NAT
For HER2‑positive IDC patients who received NAT, achieved an excellent response, but had a macrometastasis in one of four sentinel lymph nodes removed (and who will receive whole‑breast radiotherapy), the options for additional axillary treatment were as follows: radiotherapy to the axilla: 55.9% (N = 124), axillary lymph node dissection plus radiotherapy to the axilla: 26.7% (N = 59) and axillary lymph node dissection alone: 17.4% (N = 39) (Table 2, Figure 1).
Scenario 3: TN IDC, SLNB with one lymph node showing macrometastasis post‑NAT
Similar to the previous scenario, for patients with TN IDC with a macrometastasis in a sentinel lymph node post‑NAT (and who will receive whole breast radiotherapy), the additional axillary treatment options were as follows: radiotherapy to the axilla: 47.7% (N = 106), axillary lymph node dissection plus radiotherapy to the axilla: 31.5% (N = 70) and axillary lymph node dissection alone: 20.8% (N = 46) (Table 2, Figure 2).
Commercial availability of targeted therapies in Latin America
CDK4/6 and PARP inhibitors
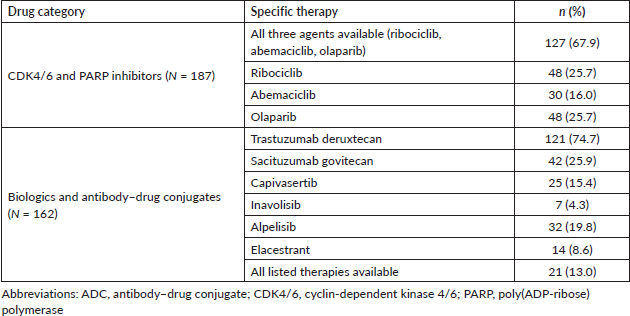
Among the 187 respondents who answered this section, 67.9% (N = 127) reported that ribociclib, abemaciclib and olaparib were marketed in their countries. Individually, availability was reported as follows: ribociclib: 25.7% (N = 48), abemaciclib: 16.0% (N = 30) and olaparib: 25.7% (N = 48) (Table 3).
Table 2. Axillary management strategies for HER2-positive and triple-negative breast cancer with residual macrometastatic nodal disease after neoadjuvant therapy
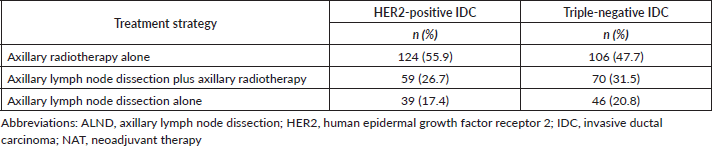
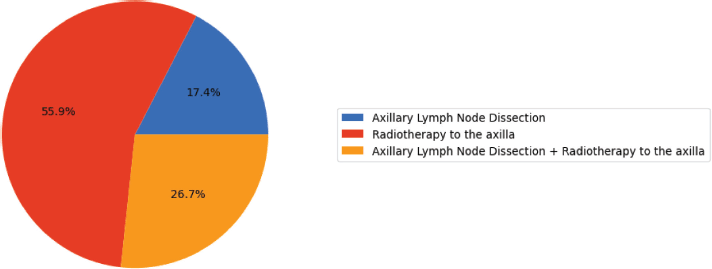
Figure 1. Axillary management strategies for HER2-positive IDC with residual macrometastatic nodal disease after NAT.
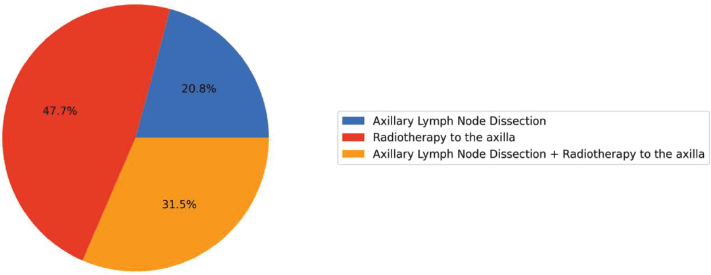
Figure 2. Axillary management strategies for TN IDC with residual macrometastatic nodal disease after NAT.
Table 3. Reported availability of targeted therapies for breast cancer in Latin America
Biologics and antibody–drug conjugates
Among the 162 respondents who answered this section, availability was reported as follows: Trastuzumab deruxtecan: 74.7% (N = 121), sacituzumab govitecan: 25.9% (N = 42), capivasertib: 15.4% (N = 25), inavolisib: 4.3% (N = 7), alpelisib: 19.8% (N = 32) and elacestrant: 8.6% (N = 14). A total of 13.0% (N = 21) of specialists reported that all of these therapies (trastuzumab deruxtecan, sacituzumab govitecan, capivasertib, inavolisib, alpelisib and elacestrant) were marketed in their countries (Table 3).
Discussion
This panregional LABCA survey provides a valuable snapshot of current practices in breast cancer management and access to innovative therapies in Latin America, covering 20 countries and the perspectives of 223 leading specialists. The findings reveal variable adoption of recommended practices and notable disparities in drug availability.
The use of functional imaging studies to assess response to NAT, particularly MRI, is widely supported by international guidelines for evaluating treatment response and planning surgery post‑NAT [5–7]. The fact that nearly two‑thirds of specialists routinely use these tools suggests a tendency towards evidence‑based practices, although one‑third still do not, which may reflect limitations in access to technology or expertise.
Regarding axillary management, the marking of metastatic lymph nodes before NAT in cN1 patients is a widely debated topic worldwide, with supporters and detractors of this practice [8–11]. In the United States, some groups perform it while others do not; in Italy, most groups do not mark the nodes and in Germany, national guidelines recommend marking up to two nodes with cytological verification of disease. This global diversity in the marking of axillary metastatic adenopathies is also reflected in Latin America, considering that 57.1% of surveyed respondents do not do it routinely. Those who argue for the necessity of node marking state that it is essential for identifying the initially positive node, reduces the rate of false negatives and may guide targeted axillary dissection (TAD) in patients who achieve a complete axillary response [12]. Similarly, various studies demonstrate the importance of identifying residual disease and its impact on the indication for adjuvant therapies in certain subgroups [13–17]. On the other hand, those who argue against its necessity base their argument on studies comparing SLNB versus TAD, showing that axillary recurrences for both groups are below 2% when there is a complete axillary response [18]. Recently at SABCS 2025, results from the primary objectives of the AXillary Surgery After NeoAdjuvant treatment study were presented [19]. Dr Thomas Kuehn from the European Breast Cancer Research Association of Surgical Trialists Network presented the results comparing SLNB versus TAD, demonstrating that there is no difference in axillary recurrence‑free survival at 3 years (SLNB 99.8% (95% CI = 99.3%–100.0%) versus TAD 98.5% (95% CI = 97.6%–99.4%)), and the subtle differences between the groups were not reflected in any oncological endpoints (local, distant, regional or axillary recurrences and overall survival).
The variability in axillary management post‑NAT, even in specific clinical scenarios, highlights the complexity of these decisions. In the case of HR‑positive patients, cN1 pre‑NAT with pCR in the sentinel lymph node (ypN0(sn)), the decision to irradiate or not regional nodes shows a notable division. While 53.9% opt for irradiation, 46.1% believe that breast irradiation is sufficient, which may reflect different interpretations of the evidence or an adaptation to the availability of radiotherapy services. Current guidelines are becoming increasingly conservative regarding radiotherapy to the axilla in cases of excellent pathological response, but the precise indications may still vary [20, 21].
For HER2‑positive and TN patients with residual macrometastasis in a SLNB post‑NAT, the discussion on whether to perform axillary dissection, axillary irradiation or both is critical. The larger proportion of specialists opting for radiotherapy to the axilla (55.9% in HER2+ and 47.7% in TN breast cancer) suggests a trend towards preferring less invasive surgical treatments than complete dissection, as long as radiotherapy is considered capable of offering comparable locoregional control. However, the persistence of a significant proportion still choosing axillary dissection or a combination of both underscores the lack of unanimous consensus and the need for better risk stratification and regionally adapted clinical guidelines for these challenging scenarios. Evidence from recent clinical trials continues to refine these recommendations, but their implementation in daily practice may be a gradual process [5].
The analysis of the marketing of targeted therapies reveals a landscape with significant differences. While 67.9% report the availability of CDK4/6 inhibitors (ribociclib and abemaciclib) and the PARP inhibitor (olaparib), indicating a good penetration of these therapies in the region for eligible patients, the individual percentages suggest that not all countries have access to the full range of drugs. The penetration of trastuzumab deruxtecan, approved for the treatment of advanced HER2‑positive and HER2‑low breast cancer, is promising with 74.7% availability [22–24]. However, other newer therapies or those for specific cases, such as sacituzumab govitecan (25.9%) [25], capivasertib (15.4%) [26], inavolisib (4.3%) [27], alpelisib (19.8%) [28] and elacestrant (8.6%) [29], show considerably lower availability. This highlights persistent barriers to access to innovation in Latin America, which may include slow regulatory processes, high costs or lack of policies based on the results of recent studies. These disparities in access to innovative drugs can directly impact oncologic outcomes for patients in different countries in the region, exacerbating inequalities in cancer care.
Limitations
The first limitation that should be emphasised is that the cross-sectional design captures only a single point-in-time snapshot of self-reported practices; practices and drug availability may have changed since data collection. Second, the use of a non-probabilistic, purposive sampling strategy through LABCA networks may over-represent academic centres and high-volume practices with more favourable access to innovative therapies, limiting generalisability to the full spectrum of practice across Latin America. Third, the survey did not stratify respondents by practice setting (public versus private sector), which is a relevant dimension of access to care; differences in clinical practices and therapeutic access between these settings were not captured and represent an important direction for future research. Fourth, although the survey included specialists across four disciplines (medical oncology, breast surgery, radiation oncology and pathology), the analysis did not stratify responses by specialty; specialty-specific differences in practice patterns, particularly relevant for axillary management decisions, could not be explored. Fifth, the survey was not designed to capture the reasons underlying clinical decisions (e.g., technology availability, reimbursement policies, local guidelines and training), nor the clinical outcomes associated with reported practices. Sixth, reported drug availability reflects specialist perception rather than formal regulatory approval or market authorisation data and should be interpreted as a proxy for real-world access at the point of care.
Conclusions
This LABCA panregional survey reveals a nuanced picture of breast cancer practice in Latin America: high adoption of functional imaging for NAT response assessment coexists with substantial variability in post-NAT axillary management and stark disparities in access to novel targeted agents. These findings carry concrete implications. First, the variability in post-NAT axillary decisions – particularly regarding nodal irradiation after sentinel lymph node biopsy – underscores the need for LABCA-led regional consensus guidelines that account for local resource realities while aligning with international evidence. Second, the markedly low availability of several agents (sacituzumab govitecan, inavolisib and elacestrant) calls for coordinated advocacy targeting regulatory agencies, health technology assessment bodies and payers across the region. Third, the multi-specialty respondent pool highlights the value of structured multidisciplinary tumour board models to standardise decision-making. Finally, future surveys should stratify by practice setting (public versus private), specialty and country income group to enable more targeted policy interventions. These results reinforce LABCA’s essential role in generating regionally relevant evidence and translating it into actionable education and health policy.
Acknowledgments
The authors thank all the specialists who took the time to respond to the survey and share their experience and knowledge. They also thank the nearly 200 attendees at the in‑person Ancillary Meeting on Breast Cancer in Latin America at the San Antonio Breast Cancer Symposium 2025, ‘From evidence to daily practice based on access’. They acknowledge the Latin American Breast Cancer Association for facilitating the distribution of the survey and supporting this research.
Conflicts of interest
The authors declare that they have no conflicts of interest.
Funding
No specific funding was received for this study. The survey was conducted using resources from the Latin American Breast Cancer Association.
Artificial intelligence disclosure statement
Artificial intelligence tools were used to assist in the creation of figures and tables in this manuscript. The authors reviewed, verified and take full responsibility for the accuracy and content of all generated materials.
Author contributions
Victor Acosta Marín: Study conception and design, data analysis and interpretation, manuscript drafting and critical revision, final approval.
Fernando Petracci: Study design, data collection coordination, statistical analysis, manuscript drafting and critical revision, final approval.
Denis U Landaverde: Study design, data interpretation, manuscript drafting and critical revision, final approval.
William Mantilla: Data collection, manuscript review, final approval.
Cynthia Villarreal: Data collection, manuscript review, final approval.
Guianeya Santander: Data collection, manuscript review, final approval.
Agatha Reyes: Data collection, manuscript review, final approval.
Joel Moreno: Data collection, manuscript review, final approval.
Ahmad Wali Mushtaq: Data collection, manuscript review, final approval.
Brizio Moreno: Data collection, manuscript review, final approval.
Juan Carlos Samamé: Data collection, manuscript review, final approval.
All authors read and approved the final manuscript.
Trial registration
Not applicable. This was a survey‑based study and not a clinical trial.
References
1. Bray F, Laversanne M, and Sung H, et al (2022) Global cancer statistics 2022: gLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries CA Cancer J Clin 74(3) 229–263 [https://doi.org/10.3322/caac.21834]
2. Mantilla W, Gonzalez M, and Rojas S, et al (2024) Significance of pathologic response in patients with early and locally advanced breast cancer treated with neoadjuvant chemotherapy in a middle income country. A real world historical cohort JCO Glob Oncol 10 e2300187 https://doi.org/10.1200/GO.23.00187
3. Saldivia F and Acosta Marín V (2025) Manejo de la axila en pacientes con cáncer de mama: consenso Nacional de la Sociedad Venezolana de Mastología Gac Méd Caracas 133(4) 1278–1295 https://doi.org/10.47307/GMC.2025.133.4.29
4. Acosta Marin V, Acosta Freites V, and Ramírez A, et al (2022) Manejo de axila posneoadyuvancia en pacientes con cáncer de mama y axila previamente positiva Rev Venez Oncol 34(4) 184–192
5. Burstein HJ, Curigliano G, and Gnant M, et al (2025) Tailoring treatment to cancer risk and patient preference: the 2025 St Gallen International Breast Cancer Consensus Statement on individualizing therapy for patients with early breast cancer Ann Oncol 36(12) 1433–1446 https://doi.org/10.1016/j.annonc.2025.09.007 PMID: 41072918
6. Álvarez-Benito M (2024) Imaging evaluation of neoadjuvant breast cancer treatment: where do we stand? Eur Radiol 34(10) 6271–6272 https://doi.org/10.1007/s00330-024-10799-0 PMID: 38753195 PMCID: 11399156
7. Van Der Voort A, Van Der Hoogt KJJ, and Wessels R, et al (2024) Diffusion weighted imaging in addition to contrast enhanced MRI in identifying complete response in HER2 positive breast cancer Eur Radiol 34(12) 7994–8004 https://doi.org/10.1007/s00330-024-10857-7 PMID: 38967659 PMCID: 11557627
8. National Comprehensive Cancer Network (2026) NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®): Breast Cancer Version 1.2026 (Fort Washington: National Comprehensive Cancer Network) [https://www.nccn.org/guidelines/guidelines-by-cancer-site/breast-cancer] Date accessed: 12/03/26
9. Reimer T, Kuehn T, and Mueller V, et al (2025) AGO Breast Commission recommendations for the surgical therapy of breast cancer: working Group on Gynecologic Cancers (AGO) update 2025 Eur J Surg Oncol 51(11) 110445 https://doi.org/10.1016/j.ejso.2025.110445 PMID: 40983010
10. Banys-Paluchowski M, Gasparri ML, and De Boniface J, et al (2021) Surgical management of the axilla in clinically node positive breast cancer patients converting to clinical node negativity through neoadjuvant chemotherapy: current status, knowledge gaps, and rationale for the EUBREAST-03 AXSANA Study Cancers (Basel) 13(7) 1565 https://doi.org/10.3390/cancers13071565 PMID: 33805367 PMCID: 8037995
11. Banys-Paluchowski M, Untch M, and Krawczyk N, et al (2023) Current trends in diagnostic and therapeutic management of the axilla in breast cancer patients receiving neoadjuvant therapy: results of the German wide NOGGO MONITOR 24 survey Arch Gynecol Obstet 307(5) 1547–1556 https://doi.org/10.1007/s00404-022-06804-w PMCID: 10110637
12. Boughey JC, Ballman KV, and Le-Petross HT, et al (2016) Identification and resection of clipped node decreases the false negative rate of sentinel lymph node surgery in patients presenting with node positive breast cancer (T0 T4, N1 N2) who receive neoadjuvant chemotherapy: results from ACOSOG Z1071 (Alliance) Ann Surg 263(4) 802–807 https://doi.org/10.1097/SLA.0000000000001375
13. Geyer CE Jr, Garber JE, and Gelber RD, et al (2022) Overall survival in the OlympiA phase III trial of adjuvant olaparib in patients with germline pathogenic variants in BRCA1/2 and high risk, early breast cancer Ann Oncol 33(12) 1250–1268 https://doi.org/10.1016/j.annonc.2022.09.159 PMID: 36228963 PMCID: 10207856
14. Rogers C, Cobb AN, and Lloren JIC, et al (2024) National trends in neoadjuvant chemotherapy utilization in patients with early stage node negative triple negative breast cancer: the impact of the CREATE X trial Breast Cancer Res Treatment 203(2) 317–328 https://doi.org/10.1007/s10549-023-07114-8
15. Mamounas EP, Untch M, and Mano MS, et al (2021) Adjuvant T DM1 versus trastuzumab in patients with residual invasive disease after neoadjuvant therapy for HER2 positive breast cancer: subgroup analyses from KATHERINE Ann Oncol 32(8) 1005–1014 https://doi.org/10.1016/j.annonc.2021.04.011 PMID: 33932503
16. Hortobagyi GN, Lacko A, and Sohn J, et al (2025) A phase III trial of adjuvant ribociclib plus endocrine therapy versus endocrine therapy alone in patients with HR positive/HER2 negative early breast cancer: final invasive disease free survival results from the NATALEE trial Ann Oncol 36(2) 149–157 https://doi.org/10.1016/j.annonc.2024.10.015
17. Johnston SRD, Harbeck N, and Hegg R, et al (2020) Abemaciclib combined with endocrine therapy for the adjuvant treatment of HR+, HER2-, node positive, high risk, early breast cancer (monarchE) J Clin Oncol 38(34) 3987–3998 https://doi.org/10.1200/JCO.20.02514 PMID: 32954927 PMCID: 7768339
18. Montagna G, Mrdutt MM, and Sun SX, et al (2024) Omission of axillary dissection following nodal downstaging with neoadjuvant chemotherapy JAMA Oncol 10(6) 793–798 https://doi.org/10.1001/jamaoncol.2024.0578 PMID: 38662396 PMCID: 11046400
19. Kühn T, Banys-Paluchowski M, and Ditsch N, et al (2025) GS2-01. More versus less invasive axillary surgical staging procedures in breast cancer patients converting from a clinically node positive to a clinically node negative stage through neoadjuvant chemotherapy -- primary endpoint analysis of the international prospective multicenter AXSANA/EUBREAST 3(R) study In San Antonio Breast Cancer Symposium (San Antonio: American Association for Cancer Research)
20. Mamounas EP, Bandos H, and White JR, et al (2025) Omitting regional nodal irradiation after response to neoadjuvant chemotherapy N Engl J Med 392(21) 2113–2124 https://doi.org/10.1056/NEJMoa2414859 PMID: 40466065 PMCID: 12269788
21. De Lima F, Pacheco C, Saldivia F, et al (2025) Recomendaciones de la Sociedad Venezolana de Mastología sobre radioterapia para el abordaje axilar en pacientes con cáncer de mama Gac Méd Caracas 133(4) 1269–1277. https://doi.org/10.47307/GMC.2025.133.4.28
22. Cortés J, Hurvitz SA, and Im SA, et al (2024) Trastuzumab deruxtecan versus trastuzumab emtansine in HER2 positive metastatic breast cancer: long term survival analysis of the DESTINY Breast03 trial Nat Med 30(8) 2208–2215 https://doi.org/10.1038/s41591-024-03021-7 PMID: 38825627 PMCID: 11333275
23. Loibl S, Park YH, and Shao Z, et al (2026) Trastuzumab deruxtecan in residual HER2 positive early breast cancer N Engl J Med 394(9) 845–857 [https://doi.org/10.1056/NEJMoa2514661]
24. Modi S, Jacot W, and Yamashita T, et al (2022) Trastuzumab deruxtecan in previously treated HER2 low advanced breast cancer N Engl J Med 387(1) 9–20 https://doi.org/10.1056/NEJMoa2203690 PMID: 35665782 PMCID: 10561652
25. Bardia A, Rugo HS, and Tolaney SM, et al (2024) Final results from the randomized phase III ASCENT clinical trial in metastatic triple negative breast cancer and association of outcomes by human epidermal growth factor receptor 2 and trophoblast cell surface antigen 2 expression J Clin Oncol 42(15) 1738–1744 https://doi.org/10.1200/JCO.23.01409 PMID: 38422473 PMCID: 11107894
26. Tokunaga E, Iwata H, Itoh M, et al (2025) Capivasertib and fulvestrant for patients with HR positive/HER2 negative advanced breast cancer: analysis of the subgroup of patients from Japan in the phase 3 CAPItello 291 trial Breast Cancer 32(1) 132–143 https://doi.org/10.1007/s12282-024-01640-z PMCID: 11717841
27. Turner NC, Im SA, and Saura C, et al (2024) Inavolisib based therapy in PIK3CA mutated advanced breast cancer N Engl J Med 391(17) 1584–1596 https://doi.org/10.1056/NEJMoa2404625 PMID: 39476340
28. André F, Ciruelos EM, and Juric D, et al (2021) Alpelisib plus fulvestrant for PIK3CA mutated, hormone receptor positive, human epidermal growth factor receptor 2 negative advanced breast cancer: final overall survival results from SOLAR 1 Ann Oncol 32(2) 208–217 https://doi.org/10.1016/j.annonc.2020.11.011
29. Bidard FC, Kaklamani VG, and Neven P, et al (2022) Elacestrant (oral selective estrogen receptor degrader) versus standard endocrine therapy for estrogen receptor positive, human epidermal growth factor receptor 2 negative advanced breast cancer: results from the randomized phase III EMERALD trial J Clin Oncol 40(28) 3246–3256 https://doi.org/10.1200/JCO.22.00338 PMID: 35584336 PMCID: 9553388
Appendix 1
The following table documents compliance with the CROSS reporting guidelines.